
About Celiac Disease
Celiac disease is a genetic autoimmune disorder driven by eating gluten. It damages the small intestine. To understand this condition, it helps to know the meaning of some key terms.
- Genetic: Related to genes. Genes are passed from parents to children and contain DNA instructions that affect how the body develops and works.
- Immune system: The body’s defense system that protects us from harmful microorganisms such as bacteria and viruses.
- Autoimmune disease: A disease where the immune system mistakenly attacks healthy parts of the body.
- Small intestine: Part of the digestive system where food is broken down and nutrients like vitamins, minerals and glucose are absorbed into the body.
- Gluten: A protein found in certain grains such as wheat, barley, rye and triticale (a mix of wheat and rye).
Celiac disease involves genes, the immune system, and the digestive system. When someone with celiac disease eats gluten, their immune system reacts as if gluten is harmful. This reaction causes inflammation and damages the lining of the small intestine.
Damage to the small intestine can make it harder for the body to digest food and absorb nutrients such as fat, iron, folate and calcium. Inflammation may also affect other organs, such as the liver or joints. Because of this, celiac disease can cause many different symptoms.
About 1% of people in Canada have celiac disease, but many remain undiagnosed. Celiac disease can develop at any age in people who have certain genes linked to the condition. However, having the genes does not mean that a person will develop celiac disease. Researchers are still learning why some people develop celiac disease while others do not.
People with celiac disease may have many symptoms, only a few, or sometimes none at all. Symptoms can range from mild to severe.
Current research indicates that 1% of the global population will contract the condition, Celiac disease can switch on at any age in either gender if they have the HLA DQ2 or DQ8 genes. It is unknown at this time what causes the disease to activate in some or not in others with the genes. People with celiac disease may have many symptoms, only a few, or sometimes none. The symptoms can range from mild to severe and last from hours to up to a week.
Myths & Facts
There are a lot of myths and misinformation about celiac disease and what it means to live a safe, healthy gluten-free life. Below are some common myths with the facts, straight from our experts.
MYTH: Celiac disease is rare in Canada.
FACT: Recent research has revealed that celiac disease affects approximately one percent of people in worldwide. Growing awareness of the disease, earlier diagnosis and excellent blood screening tests point to the likelihood of similar prevalence figures in Canada.
MYTH: Celiac disease is easily recognized.
FACT: Celiac disease can be difficult to recognize since symptoms are often vague and nonspecific. Symptoms can vary greatly from person to person and can appear at any age.
MYTH: A trial of the gluten-free diet is a good way of selecting patients who have celiac disease.
FACT: A gluten-free diet should not be started until the diagnosis of celiac disease has been made by the screening blood test and a small bowel biopsy. A trial of the gluten-free diet before the blood tests and the biopsy allows the villous damage to improve which may make the interpretation of the tests inconclusive and further delay the diagnosis of celiac disease. Moreover, patients may respond clinically to dietary changes for reasons other than celiac disease.
MYTH: Celiac disease can be diagnosed by a simple blood test.
FACT: Blood screening tests (EMA or tTG) may suggest that a person has celiac disease, but they do not replace the need for an intestinal biopsy. Intestinal biopsies are the only definitive means of diagnosing celiac disease.
MYTH: An intestinal biopsy is a major surgical procedure requiring general anesthesia.
FACT: This procedure is performed under sedation by an experienced specialist and is usually done as an outpatient procedure. In children, sedation or anesthetic may be used.
MYTH: Celiac disease and dermatitis herpetiformis are unrelated.
FACT: Dermatitis herpetiformis (DH) is celiac disease of the skin. Persons with dermatitis herpetiformis may or may not have intestinal symptoms characteristic of celiac disease, but they will have an abnormal small bowel biopsy. Treatment of dermatitis herpetiformis requires a gluten-free diet for life and medication to help relieve the burning and itching of the skin rash.
MYTH: Celiac disease is a childhood disease.
FACT: Celiac disease is an inherited condition, and symptoms may develop at any age after the ingestion of gluten.
MYTH: Celiac disease can be outgrown.
FACT: Celiac disease is a life-long disease. Eating food containing gluten will continue to damage the intestinal lining and will increase the risk of developing associated conditions and other complications. The only known treatment for celiac disease is a gluten-free diet for life.
MYTH: A person with celiac disease needs to avoid only wheat and wheat products.
FACT: Effective treatment of celiac disease requires strict avoidance of gluten ingestion for life. The gluten found in various wheats (e.g., durum, kamut, spelt), and in rye, barley, triticale, and regular oats* must be avoided. Consultation with a registered dietitian is recommended to learn about the hidden sources of gluten and how to prepare a nutritious, well balanced diet while avoiding gluten. Only oats labelled gluten free may be consumed by a person with celiac disease. Oats, while not containing the gluten protein, are highly likely to come into contact with gluten-containing grains (wheat, rye) during growing and harvesting.
MYTH: A person with celiac disease can tolerate a small amount of dietary gluten, including Europe once in a while.
FACT: Even though some people with celiac disease may seem to tolerate gluten, damage is still being done to the intestinal lining when gluten is eaten Treatment for celiac disease is a strict gluten-free diet for life. Wheat is wheat and it causes intestinal damage and inflamation.
MYTH: Oats are allowed on a gluten-free diet.
FACT: The safety of oats in celiac disease has been extensively investigated. Clinical studies have shown that pure, uncontaminated oats are safe for most adults and children with celiac disease. Most commercially available oats are contaminated with wheat or barley. However, individuals with celiac disease must ensure that the oats they are eating are free from gluten contamination.
MYTH: After diagnosis and adherence to a “gluten- free diet”, a person with celiac disease can be considered “cured” and needs no further medical or dietary supervision.
FACT: There is no current cure for celiac disease. At the moment, once your diagnosed with the active disease, you will need to remain on a strict gluten-free diet for life in order for the intestinal villi to heal and reduce inflammation. Follow up with your physician and dietitian is recommended. Check out our follow-up management link with information you can take to your medical professional.
Screening
Screening for celiac disease is recommended for any person, child or adult experiencing symptoms associated with the condition or if the person is at higher risk of developing celiac disease. Celiac screening may be inaccurate among children less than 2 years of age. Routine screening among individuals at higher risk for celiac disease is recommended, including:
- First- and second-degree family members (parents, siblings, children, grandparents, aunt, uncle, niece, nephew) of a person with celiac disease
- Celiac disease is a genetic disorder, meaning that if you have celiac disease, you carry the HLA DQ2, DQ7 and/or DQ8 gene inherited by one or both of your parents. Therefore, first and second-degree family members of a person with celiac disease have a higher risk of celiac disease
- Genetic testing may be performed to rule out celiac disease. It is not used for diagnosis
- People with another autoimmune disease, such as type 1 diabetes, Hashimoto’s thyroiditis or Grave’s disease, inflammatory bowel disease (IBD), rheumatoid arthritis, lupus and Sjӧgren’s syndrome.
- People with chromosomal disorders such as Down syndrome, William Syndrome or Turner syndrome.
- People with immunoglobulin A (IgA) deficiency or IgA nephropathy
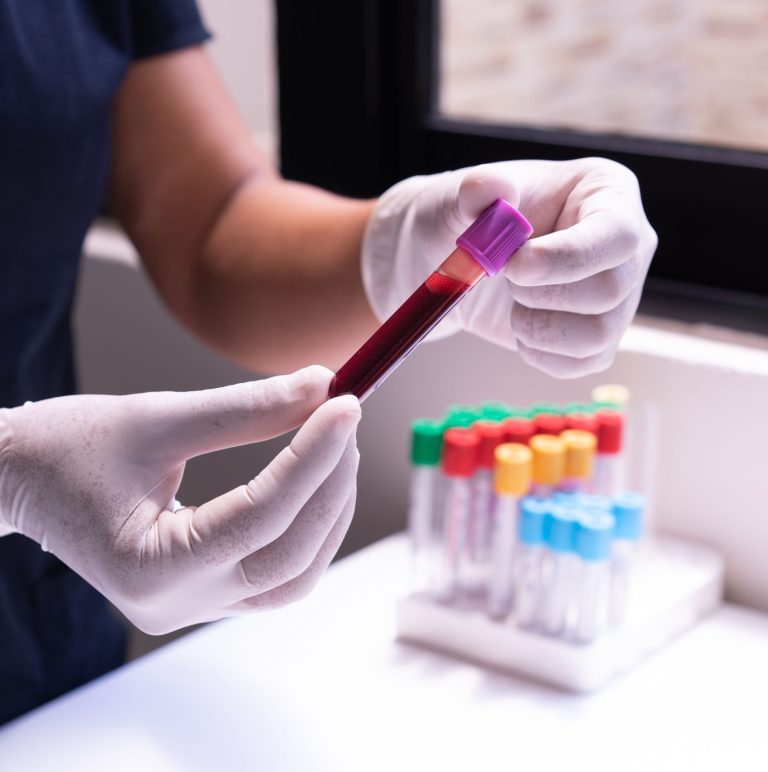
Screening for celiac disease is done through a blood test. This test can be ordered by health care professionals such as your family doctor, nurse practitioner or a naturopath. In the medical community, this screening is called serological testing, which uses one or more antibody tests. The main test is called tissue transglutaminase IgA (tTG‑IgA). When screening for celiac disease, a total IgA test must also be done to make sure the body can produce IgA. If a person cannot make IgA, the tTG‑IgA test may not be accurate. People who cannot make IgA have a condition called IgA deficiency, and in these cases, different tests—such as tTG‑IgG—can be used instead. IgA deficiency affects about 2–3% of people with celiac disease.
Other celiac blood tests may be ordered by gastroenterology specialists. These include:
- IgA endomysial antibody (EMA)
- This test is the most specific for celiac disease, but it is not as sensitive as the tTG-IgA test. About 5-10% of people with celiac disease will not have a positive EMA result. It is usually reserved for specific cases.
- Deamidated gliadin peptide (DGP IgA and IgG)
- This test can be used to screen for celiac disease in people with IgA deficiency, or in people who test negative for tTG or EMA antibodies
When screening for celiac disease, it is VERY important that the person is eating enough gluten every day. The celiac test is less accurate if a person is avoiding or limiting gluten-containing foods. This is because the immune system may not be making enough antibodies for the test to detect, which can lead to a “false-negative” result. This means that the test did not show celiac disease even though the person may have it. In that case, more testing may be needed to confirm the diagnosis. Early diagnosis through blood testing is important because it helps prevent long-term health problems linked to active celiac disease, such as weak bones and certain types of cancer.
Diagnosis
The diagnosis of celiac disease is confirmed through a procedure called an upper endoscopy with intestinal biopsies.
An upper endoscopy is a relatively safe procedure that usually takes less than thirty minutes. Children are usually put under general anesthesia while adults receive local anesthetics. During the procedure, a gastroenterologist inserts a small tube with a camera through the mouth and down into the small intestine. From the small intestine, the doctor takes several small samples of tissue, called biopsies. These samples are examined under a microscope by a specialist called a pathologist. The pathologist looks for signs of celiac disease, such as villous atrophy (damage and flattening of the tiny finger‑like projections in the intestine) or an increase in certain white blood cells. The lining of the intestine does not have nerve cells, so taking biopsies is not painful, but a sore throat may occur afterward from the tube.
An upper endoscopy with biopsies is considered the best way to diagnose celiac disease because:
- The tissue samples can confirm active celiac disease even if symptoms have improved
- The proceliac diseaseure can also show if another digestive condition is present

Genetic testing can not diagnose celiac disease, but it can help support the diagnosis. For people who cannot have an upper endoscopy, a gastroenterologist may suggest a video capsule endoscopy. This proceliac diseaseure uses a small camera inside a pill to take pictures of the digestive tract. However, there is not enough evidence to show that this test can fully replace results of duodenal biopsies for diagnosing celiac disease.
Some children may qualify for a diagnosis based on blood tests and may not need an upper endoscopy. This approach is not recommended by the North American Pediatric Association (NASPGHAN), but it may be used in certain cases.
For people with dermatitis herpetiformis (DH) a skin biopsy, celiac blood work and small bowel biopsies are collected to diagnose both DH and celiac disease. The skin biopsy involves taking a small sample of skin near the rash and testing it for IgA antibodies.






